





Ankylosing spondylitis: how have treatments evolved in recent years?
Published 31 Oct 2026 • By Razarutheen Mustafa
Living with ankylosing spondylitis can mean dealing with persistent back pain, morning stiffness and fatigue that affect everyday life. For years, treatment largely focused on relieving symptoms. Today, advances in biologic therapies and targeted medicines have expanded the options available to people living with this chronic inflammatory disease.
But what has really changed in ankylosing spondylitis treatment? Are newer medicines more effective, and how do doctors decide which treatment is right for each patient?
Understanding ankylosing spondylitis and its treatment goals
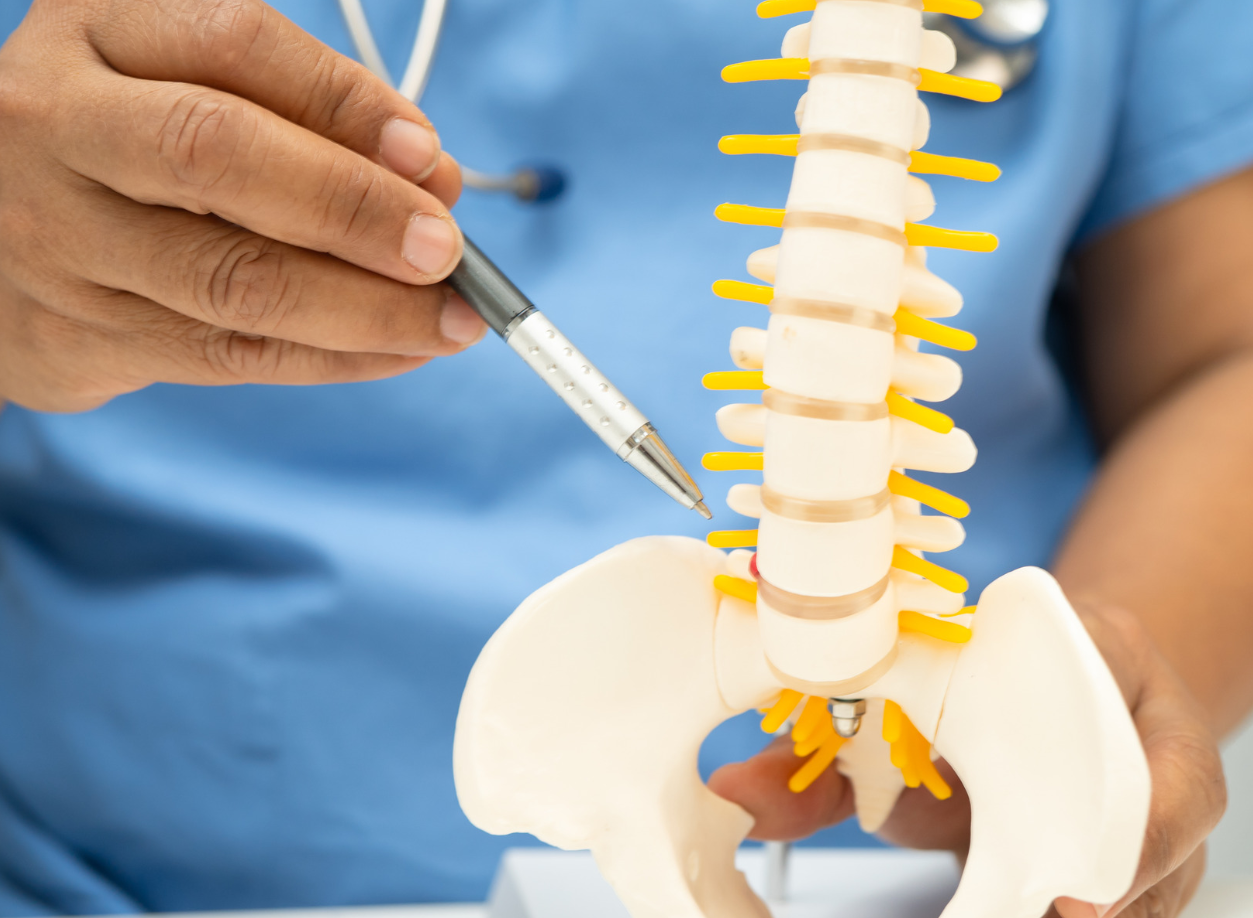
Ankylosing spondylitis (AS) is a chronic inflammatory condition that mainly affects the spine and sacroiliac joints, where the spine connects to the pelvis.
It belongs to a broader group of conditions called axial spondyloarthritis (axSpA). Ankylosing spondylitis generally refers to the form in which characteristic structural changes can be seen on X-rays.
Common symptoms include inflammatory back pain, stiffness that is often worse after rest, reduced mobility and fatigue. Some people also experience inflammation affecting the eyes, skin or digestive system.
Although there is currently no cure for ankylosing spondylitis, treatment aims to reduce inflammation, control pain and stiffness, preserve mobility and improve quality of life.
As Carenity explains in Ankylosing spondylitis: Understanding disease progression to better plan for the future, the condition does not progress in the same way for everyone. This is one reason treatment needs to be adapted to individual symptoms and disease activity.
How were ankylosing spondylitis treatments traditionally managed?
For many years, non-steroidal anti-inflammatory drugs (NSAIDs), such as naproxen and ibuprofen, have been an important first-line treatment.
They can help relieve inflammatory back pain and stiffness, making everyday movement more manageable.
However, NSAIDs do not work well enough for everyone and may cause side effects, including gastrointestinal, kidney or cardiovascular problems.
Doctors therefore consider a person's medical history, other medicines and risk factors when recommending them.
Exercise and physiotherapy have also remained essential parts of ankylosing spondylitis management. Stretching, strengthening, posture exercises and regular movement can help maintain flexibility and physical function.
For people experiencing periods of worsening symptoms, Carenity's article Ankylosing spondylitis: What are flare-ups and how can you manage them? explores ways of managing these difficult periods.
Biologic therapies: a major advance in ankylosing spondylitis treatment
One of the most important developments in recent decades has been the introduction of biologic disease-modifying antirheumatic drugs (biologic DMARDs).
Unlike conventional painkillers, these medicines target specific parts of the immune system involved in inflammation.
They may be considered when ankylosing spondylitis remains active despite appropriate first-line treatment.
TNF inhibitors: targeting a key inflammatory protein
Tumour necrosis factor (TNF) inhibitors were among the first biologic treatments to transform the management of ankylosing spondylitis.
Examples include:
- Adalimumab
- Etanercept
- Infliximab
- Golimumab
- Certolizumab pegol
These medicines block TNF, a protein involved in inflammatory processes.
For some patients, TNF inhibitors can significantly reduce pain, stiffness and disease activity while improving physical function.
However, they do not work equally well for everyone. Because they affect immune responses, patients require appropriate screening and monitoring, particularly for infections.
IL-17 inhibitors: another way to control inflammation
More recently, interleukin-17 (IL-17) inhibitors have provided an additional treatment option.
Examples include secukinumab, ixekizumab and bimekizumab.
These medicines target inflammatory pathways involving IL-17, a protein associated with inflammation in axial spondyloarthritis.
IL-17 inhibitors may be useful for certain patients whose symptoms remain active despite previous treatment, or when another biologic is considered more appropriate.
The choice of treatment also depends on associated conditions. For example, IL-17 inhibitors may be useful when significant psoriasis is present, but they are generally avoided in people with active inflammatory bowel disease because they may worsen intestinal inflammation.
There is no single biologic treatment that is best for everyone. The decision depends on disease activity, other medical conditions, previous treatment responses and potential risks.
JAK inhibitors: a newer oral treatment option
Another significant development is the introduction of Janus kinase (JAK) inhibitors, a class of targeted synthetic medicines.
Unlike most biologic treatments, which are given by injection or infusion, JAK inhibitors are taken as tablets.
Examples used for ankylosing spondylitis in the UK include upadacitinib and tofacitinib, subject to the relevant prescribing criteria.
These medicines interfere with signalling pathways involved in inflammation.
For some people with active ankylosing spondylitis who have not responded adequately to other treatments, JAK inhibitors provide an additional option.
However, they require careful consideration because they can increase the risk of serious infections and, in certain patients, blood clots, cardiovascular events and some cancers.
Before prescribing them, rheumatologists assess factors such as age, smoking history, cardiovascular risk, previous infections and other health conditions.
The availability of an oral treatment does not automatically make it safer or more suitable than an injectable medicine.
What has changed in treatment recommendations?
The 2025 British Society for Rheumatology guideline reflects how much ankylosing spondylitis care has evolved.
It recommends considering TNF inhibitors, IL-17 inhibitors or JAK inhibitors for people with active axial spondyloarthritis whose symptoms remain inadequately controlled despite appropriate conventional and non-drug treatment.
An important change is the greater emphasis on personalised treatment and shared decision-making.
Rather than focusing only on back pain, rheumatologists now consider:
- Disease activity: Pain, stiffness, fatigue and signs of ongoing inflammation.
- Previous treatment response: Whether current medicines are helping sufficiently.
- Associated conditions: Such as psoriasis, uveitis or inflammatory bowel disease.
- Safety considerations: Including infection risk and other medical conditions.
- Personal priorities: Mobility, work, family responsibilities and quality of life.
Another development is the wider use of biosimilars, which are highly similar versions of approved biologic medicines. They meet regulatory standards for comparable quality, safety and effectiveness and may improve access to treatment.
If one advanced treatment is ineffective or causes unacceptable side effects, a rheumatologist may consider switching to another medicine or treatment class after reassessing the situation.
Are exercise and physiotherapy still important?
Absolutely. Despite advances in medication, physical activity and physiotherapy remain central to ankylosing spondylitis treatment.
Medicines can help control inflammation, while exercise supports posture, mobility, strength and everyday function.
Depending on individual needs, a physiotherapist may recommend stretching, strengthening, breathing exercises, swimming or other suitable activities.
Carenity also explores lifestyle considerations in The effects of diet on ankylosing spondylitis.
Although a balanced diet supports general health, no specific diet has been proven to replace medical treatment for ankylosing spondylitis.
When should you discuss changing your treatment with your rheumatologist?
If pain, morning stiffness or fatigue continues to interfere with daily activities despite treatment, it may be time for a review.
You do not have to wait until symptoms become unbearable to raise concerns.
Before your appointment, consider noting:
- Pain and stiffness: Their severity, duration and impact on daily life.
- Flare-ups: How frequently they occur and how long they last.
- Mobility: Any changes in movement, posture or physical activities.
- Current medicines: Benefits, side effects and any missed doses.
- Other symptoms: Eye inflammation, skin changes or digestive problems.
- Personal goals: Activities you would like to manage more comfortably.
You could ask your rheumatologist whether your disease activity needs reassessing, whether your current treatment is achieving its goals and whether another option might be appropriate.
If you take biologic or JAK inhibitor treatment, report signs of infection promptly and follow your specialist team's advice. Seek urgent assessment for a painful, red eye with light sensitivity or changes in vision, which may indicate uveitis.
Never stop or change prescribed treatment without discussing it with your healthcare team.
Living with ankylosing spondylitis: learning from others
Treatment decisions can feel complicated, particularly when several medicines are available and responses vary between patients.
The Carenity UK ankylosing spondylitis community offers a space to discuss symptoms, treatments and daily challenges with others living with the condition.
Members have also shared their experiences in discussions such as What medication are you on for your AS?.
Reading these experiences may help you prepare questions for your next rheumatology appointment. However, another person's response to a medicine does not predict how it will work for you.
A more personalised future for ankylosing spondylitis care
The evolution of ankylosing spondylitis treatment has brought more choices, from established anti-inflammatory medicines to biologic therapies and newer targeted treatments.
For many patients, these advances offer additional ways to manage inflammation, improve mobility and maintain quality of life.
The most important progress is not simply having more medicines available. It is being able to choose and adjust treatment according to each person's needs, symptoms and priorities.
Frequently Asked Questions
1. What is the latest treatment for ankylosing spondylitis?
Newer options include IL-17 inhibitors such as bimekizumab and oral JAK inhibitors such as upadacitinib. Suitability depends on individual circumstances and UK prescribing guidance.
2. Are biologics better than NSAIDs for ankylosing spondylitis?
They have different roles. NSAIDs are generally used first, while biologics may be recommended when disease activity remains high despite appropriate initial treatment.
3. Can ankylosing spondylitis be cured?
There is currently no cure, but modern treatments can reduce inflammation, relieve symptoms and help preserve physical function.
4. What happens if a biologic treatment stops working?
Your rheumatologist may reassess your disease activity, investigate other causes of symptoms and consider switching to another biologic or targeted medicine.
5. Do you still need exercise when taking biologics?
Yes. Regular, appropriately tailored exercise and physiotherapy remain important for maintaining mobility, posture and overall physical health.
If you found this article helpful, feel free to give it a “Like” and share your thoughts or experiences with the community in the comments below!
Take care!
 Facebook
 Twitter
Sources:




